Signed in as:
filler@godaddy.com
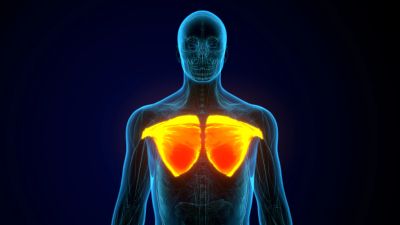
This program is designed for surgically repaired pectoralis major (PM) tendon rupture (the most common scenario requiring structured rehab) but is adaptable to conservatively-managed partial tears with slower progression. It synthesises orthopaedic surgical literature, sports physiotherapy expert consensus, and recent scoping reviews. Current evidence consistently supports early surgical repair combined with an accelerated, phased rehabilitation protocol for optimal strength recovery and return to sport (RTS).
· Key Evidence Points
· · Accelerated, phased rehab after early surgical repair reliably restores strength and function.
· · Sling protection 4–6 weeks with pendular/passive ROM; active motion from ~4 weeks; resistance from ~6 weeks.
· · Contact/collision sport RTS 4–7 months to full pre-injury level of sport more broadly.
· · Tendon-to-bone fixation technique and early repair are preferred — better functional outcomes and RTS rates.
──────────────────────────────────────────────────
Goals: Protect repair, control pain/oedema, prevent elbow stiffness, educate patient.
· Broad arm sling worn across the body continuously for the first 4–6 weeks.
· Pendular exercisesonly (minor, gravity-assisted).
· Passive shoulder ROM (PROM) to tolerance, maintaining sling between exercises.
· Cryotherapy, posture re-education, scapular setting.
· Avoid: active shoulder flexion, abduction, external rotation, pushing, pulling, lifting.
· Wound care per surgeon protocol.
──────────────────────────────────────────────────
Goals: Progress PROM, restore scapular control, commence isometric activation.
· Continue sling use (wean from week 4–6 per surgeon guideline).
· Progressive PROM of glenohumeral joint in supine/gravitationally-assisted positions.
· Isometric shoulder adduction and internal rotation sub-maximal — introduced around week 3.
· Active-assisted ROM (AAROM) with stick.
· Scapulothoracic retraction/protraction isometrics, postural control.
· Cervical and elbow mobility maintenance.
· Avoid: resisted adduction/IR, eccentric PM loading, weight bearing through the arm.
──────────────────────────────────────────────────
Goals: Restore rotator cuff and scapular stabiliser strength, initiate PM activation, achieve full painless AROM.
· Sling weaned (most protocols by 6 weeks).
· Rotator cuff strengthening supervised by physiotherapist from 6 weeks.
· Isotonic scapular stabiliser work (rows, low-load serratus punches).
· Closed-chain PNF and D2 patterns progressing to open-chain.
· Isokinetic testingbaseline from ~10–12 weeks to quantify strength deficits (useful given adduction/internal rotation are PM functions).
· Avoid: maximal adduction/IR, bench press mechanics, heavy horizontal pushing.
──────────────────────────────────────────────────
Goals: Symmetrical strength, functional capacity, sport-specific loading introduction.
· Light strength training from ~3 months, progressive strength training from ~4 months with physiotherapy supervision.
· Progressive PM activation: from low-load isometrics → concentric isotonics → isokinetic adduction/IR training.
· Full kinetic chain work (hips, core, thoracic mobility).
· Isokinetic strength testing at 6 months (90°/s) — monitor adduction deficit (19–25% typical at this stage, expected to improve).
· Reintroduce unilateral bench press mechanics only when adduction strength ≥80% of contralateral.
──────────────────────────────────────────────────
Goals: Full sport-specific performance, psychological readiness, risk-mitigation.
· Return to contact/collision training at 8–10 weeks in professional AFL after strength and pain clearance by surgeon and high-performance team.
· Full pre-injury level of sport broadly at 4–7 months post-repair.
· Bench press: reintroduce progressively from ~6 months; technique modification (flared elbows, avoiding bottom of range excess) as prevention.
· Psychosocial screening — kinesiophobia (Tampa Scale) and confidence scales (I-PRRS) recommended.
· RTS criteria — a criteria-based model (symmetry of strength, pain-free sport-specific drills, completion of high-demand functional tests) over time-based discharge.
────────────────────────────────────────────────────────────────────────────────
· Rerupture risk — 1/20 (5%) in AFL cohort within first month, often innocuous mechanism.
· Delayed presentation/surgery worsens outcome due to tendon retraction and scarring.
· Concomitant subscapularis tear is common — modify rehab to protect subscapularis repair if present.
────────────────────────────────────────
────────────────────────────────────────
1. Bak K, Cameron EA, Henderson IJ. Pectoralis major rupture: a simplified classification, repair and a report of 90 patients. J Shoulder Elbow Surg. 2000;9(5):353–360.
2. de Castro Pochini A, Andreoli CV, Belangero PS, et al. Clinical considerations for the surgical treatment of pectoralis major muscle ruptures: report of 25 cases and literature review. Int J Sports Med. 2014;35(2):125–129.
3. Cresswell TR, Smith RB. Bilateral pectoralis major rupture: a case report and review of the literature. Br J Sports Med. 1998;32(4):335–337.
4. ElMaraghy AW, Devereaux MW, Rachevsky O. Biceps tenotomy and partial pectoralis major transfer for subscapularis-insufficient shoulders: technique and outcomes in a cohort. J Shoulder Elbow Surg. 2012;21(11):e1–e6.
5. Fleury AM, Silva AC, Pochini AC, Ejnisman B, Cohen M, Mattar Júnior R. Pectoralis major muscle rupture: biomechanical analysis and repair technique. Rev Bras Ortop. 2011;46(3):273–279.
6. Merolla G, Paladini P, Artiaco S, Tos P, Lollino N, Porcellini G. Pectoralis major tendon rupture: surgical procedures and clinical outcomes. Int Orthop. 2015;39(11):2187–2195.
7. Butt U, Mehta S, MacDermid J, Ghosh G, Athwal GS. The Ochsner Pectoralis Major Repair Rehabilitation Protocol. Ochsner J. 2017;17(1):74–81.
8. Schepsis AA, Grafe HW, Jones HP, Lomasney LM. Rupture of the pectoralis major muscle: outcome after repair of acute and chronic injuries. Am J Sports Med. 2000;28(1):9–15.
9. de Castro Pochini A, Ejnisman B, Andreoli CV, et al. Pectoralis major muscle rupture in athletes: a prospective study. Am J Sports Med. 2010;38(7):1407–1412.
10. Quinlan JF, Molloy M, Hurson BJ. Pectoralis major tendon ruptures: when to operate. Br J Sports Med. 2002;36(3):226–228.
11. Wolfe SW, Wickiewicz TL, Cavanaugh JT. Ruptures of the pectoralis major muscle: an anatomic and clinical analysis. Am J Sports Med. 1992;20(5):587–593.
12. Bow JH, Saltzman MD, Mayer RA, Marwin SE, Silvis MJ, Tashjian RZ. Partial pectoralis major ruptures: presentation, imaging, treatment and outcomes: a review of the literature and 12 case reports. Iowa Orthop J. 2010;30:101–106.
13. Hart ND, Lindsey DP, McAdams TR. Pectoralis major tendon repair: a biomechanical comparison of two repair techniques. J Shoulder Elbow Surg. 2011;20(8):1231–1237.
14. Aleem AW, Syed UAM, Widmann BS, et al. Repair of pectoralis major ruptures: single- vs double-row technique. Orthopedics. 2017;40(6):e935–e939.
15. Sharma S, Whiteley R, Rani B, Sartori S, Sharma H, Gabbett TJ. Mapping the existing return-to-sport criteria after pectoralis major tendon injury in different sports: a scoping review for getting back to the game. Sports Health. 2026.
16. Sartori S, Whiteley R. Pectoralis major ruptures during rugby league tackling—case series with implications for tackling technique instruction. J Sci Med Sport. 2019;22(12):1298–1303.
17. Schwab L, Warby S, Davis K, et al. Video analysis of pectoralis major injuries in professional Australian football players. Orthop J Sports Med. 2022;10(8):23259671221117826.
18. Schwank A, Blazey P, Asker M, et al. 2022 Bern consensus statement on shoulder injury prevention, rehabilitation, and return to sport for athletes at all participation levels. J Orthop Sports Phys Ther. 2022;52(1):11–28.
19. Slobogean GP, Slobogean BL, Meek M, Garraway N, Stockton D, Wing P. Surgical versus conservative management of pectoralis major tendon ruptures: a systematic review. Open Access J Sports Med. 2015;6:35–41.
20. Yu J, Zhang C, Horner N, et al. Outcomes and return to sport after pectoralis major tendon repair: a systematic review. Sports Health. 2019;11(2):134–141.
21. Koukoumis P, Whiteley R, Engebretsen L, et al. Return to sport after pectoralis major repair: a systematic review and meta-analysis. Br J Sports Med. 2022.
22. Markwick S, Elliott J, Hayton MJ, Wallace WA. Pectoralis major tendon repair: outcomes of two surgical techniques and long-term follow-up. Bone Joint J. 2015;97-B(10):1373–1378.
23. Shah NR, Lo EY, Galdi B, et al. Outcomes after pectoralis major surgical repair: a systematic review and meta-analysis. J Shoulder Elbow Surg. 2020;29(3):615–623.